Is the Paleo Diet a Reliable Treatment for Ulcerative Colitis?

It’s not generally recognized as such, but it seemed to put a New Zealand nutritionist’s case into remission. Julianne Taylor provides the details in a guest post by Jess Fisk.

A search of the Internet will reveal many cases of apparent cure or remission of ulcerative colitis after a great variety of non-obvious interventions. I’m happy for all those folks, whether the intervention was responsible or the disease coincidentally went into “spontaneous” remission when the intervention began.

One of my go-to sources for current disease information is UpToDate.com. Most of the articles there are written by medical school professors. A quick scan of ulcerative colitis treatments reveals an overwhelming focus on surgery and drugs. Little in terms of diet except for this tidbit on elimination diets:

An elimination diet involves removing a food from the diet for a period of time and seeing whether symptoms resolve during that time. In patients receiving enteral nutrition, it involves introducing one new food at a time to identify foods that precipitate [inflammatory bowel disease] symptoms. Many patients can identify foods that they believe may precipitate or worsen their disease and it is reasonable for them to avoid such foods. Using an elimination diet to identify at-risk foods may decrease the possibility of a “flare” of [inflammatory bowel disease].

(Inflammatory bowel disease refers to both ulcerative colitis and Crohn’s disease.)

Foods that precipitate symptoms commonly included cereals, lactose, and yeast products.

Studies were contradictory or inconsistent regarding the benefits of other dietary interventions such as low carbohydrate diets, fiber, fish oil supplements, and antioxidants.

In case you’ve heard of the Specific Carbohydrate Diet, the UpToDate authors say that randomized trials are required before it can be recommended for ulcerative colitis.

I didn’t see anything about the FODMAPs diet.

With regards to dietary causes of inflammatory bowel disease (IBD), I found this at UpToDate:

Food antigens are thought to trigger an immunologic response resulting in the development of IBD. However, specific pathogenic antigens have not been identified. While studies attempting to associate specific diets with the development of IBD have had inconsistent results, the data suggest that a “Western” style diet (processed, fried, and sugary foods) is associated with an increased risk of developing Crohn’s disease, and possibly ulcerative colitis.

The next paragraph talks about implicated dietary risk factors, including hypersensitivity to cow milk protein in infancy, refined sugar, decreased vegetable and fiber intake. Also, “increased dietary intake of total fat, animal fat, polyunsaturated fatty acids, and milk protein has been correlated with an increased incidence of ulcerative colitis and Crohn’s disease and relapse in patients with ulcerative colitis. In addition, a higher intake of omega-3 fatty acids and a lower intake of omega-6 fatty acids have been associated with a lower risk of developing Crohn’s disease.”

Since the paleo diet eliminates several major food groups, it’s entirely possible it could put ulcerative colitis into remission or even cure it.

Academically oriented paleo diet gurus should get together and decide what the paleo diet is, so clinicians can start testing it scientifically.  They’re the guys who can snag the funding for studies.

Steve Parker, M.D.


First Nation Aborigines Improve Diabetes By Return to Ancestral Diet

…along with improvement in high blood pressure, weight, and heartburn. Dr. Jay Wortman worked with aborigines on the west coast of Canada, convincing some of them to return to their ancestral diet, which happened to be low in carbohydrate. Dr. Wortman shared his experience in a video with DietDoctor Andreas Eenfeldt. Or check out the hour-long documentary, “My Big Fat Diet,” which may be available on YouTube.

Dr. Wortman seems to have cured his own case of type 2 diabetes with an Atkins-style diet.

—Steve

A Theoretical Framework For Evolutionary Medicine

paleo diet, Paleolithic diet, hunter-gatherer diet

Huaorani hunter in Ecuador

If you’re scientifically inclined, you’ll enjoy perusing the following article. Otherwise, quit now before it’s too late.

“Lifestyle and nutritional imbalances associated with Western diseases: causes and consequences of chronic systemic low-grade inflammation in an evolutionary context,” by Begoña Ruiz-Núñez, Leo Pruimboom, D.A. Janneke Dijck-Brouwer, and Frits A.J. Muskiet. It’s in the Journal of Nutritional Biochemistry, vol. 24, issue 7, pp. 1183-1201. http://dx.doi.org/10.1016/j.jnutbio.2013.02.009,

Here’s the abstract:

In this review, we focus on lifestyle changes, especially dietary habits, that are at the basis of chronic systemic low grade inflammation, insulin resistance and Western diseases. Our sensitivity to develop insulin resistance traces back to our rapid brain growth in the past 2.5 million years. An inflammatory reaction jeopardizes the high glucose needs of our brain, causing various adaptations, including insulin resistance, functional reallocation of energy-rich nutrients and changing serum lipoprotein composition. The latter aims at redistribution of lipids, modulation of the immune reaction, and active inhibition of reverse cholesterol transport for damage repair. With the advent of the agricultural and industrial revolutions, we have introduced numerous false inflammatory triggers in our lifestyle, driving us to a state of chronic systemic low grade inflammation that eventually leads to typically Western diseases via an evolutionary conserved interaction between our immune system and metabolism. The underlying triggers are an abnormal dietary composition and microbial flora, insufficient physical activity and sleep, chronic stress and environmental pollution. The disturbance of our inflammatory/anti-inflammatory balance is illustrated by dietary fatty acids and antioxidants. The current decrease in years without chronic disease is rather due to “nurture” than “nature,” since less than 5% of the typically Western diseases are primary attributable to genetic factors. Resolution of the conflict between environment and our ancient genome might be the only effective manner for “healthy aging,” and to achieve this we might have to return to the lifestyle of the Paleolithic era as translated to the 21st century culture.

I encourage you to read the whole article if you’re interested in such things. I’ll only mention certain concepts in this post if I want to learn or remember them for my own purposes.

The authors stress our large brains’ constant need for energy from glucose. This is how they explain our propensity to develop insulin resistance:

A glucose deficit leads to competition between organs for the available glucose. As previously mentioned, this occurs during fasting [and starvation], but also during pregnancy and infection/inflammation. Fasting is characterized by a generalized shortage of glucose (and other macronutrients), but in case of pregnancy and inflammation we deal with active compartments competing with the brain for the available glucose, i.e., the growing child and the activated immune system, respectively. During competition between organs for glucose, we fulfill the high glucose needs of the brain by a reallocation of the energy-rich nutrients, and to that end, we need to become insulin resistant.

During starvation and times of infection or inflammation, we divert glucose to our brains or immune systems via insulin resistance in certain tissues. These tissues can then use less glucose and more fat for energy. “…the adipose tissue compartment will be encouraged to distribute free fatty acids, while the liver will be encouraged to produce glucose via gluconeogenesis and to distribute triglycerides via very low-density lipoprotein (VLDL).”

This reallocation of energy—the aim of the process above—and the compensatory hyperinsulinemia “are meant for short-term survival, and their persistence as a chronic state are at the basis of the ultimate changes that we recognize as the symptoms of the metabolic syndrome, including the changes in glucose and lipid homeostasis and and the increasing blood pressure. For example, the concomitant hypertension has been explained by a disbalance between the effects of insulin on renal sodium reabsorption and NO-mediated vasodilatation, in which the latter effect, but not the first, becomes compromised by insulin resistance, causing salt sensitivity and hypertension.”

I warned you to get out before it was too late!

Looks like a great place to hike

Looks like a great place to hike

I don’t ever recall reading how much energy our immune system uses. The authors write:

During infection/inflammation we deal with the metabolic needs of an activated immune system for acute survival. The inactive immune system consumes about 23% of our basal metabolism, of which as much as 69% derives from glucose (47%) and the glycogenic amino acid glutamine (22%). Upon activation, the energy requirement of our immune system may increase with about 9–30% of our basal metabolic rate. In multiple fractures, sepsis and extensive burns, we deal with increases up to 15–30, 50, and 100% of our basal metabolism, respectively.

The activated immune system, they say, functions mainly on glucose.

Summarizing thus far, we humans are extremely sensitive to glucose deficits, because our large brain functions mainly on glucose. During starvation, pregnancy and infection/inflammation, we become insulin resistant, along with many other adaptations. The goal is the reallocation of energy-rich substrates to spare glucose for the brain, the rapidly growing infant during the third trimester of pregnancy, and our activated immune system that also functions mainly on glucose. Under these conditions, the insulin resistant tissues are supplied with fatty acids. Other goals of the changes in the serum lipoprotein composition are their role in the modulation of the immune response by the clearance of LPS [lipopolysaccharides] during infection/inflammation and the redirection of cholesterol to tissues for local damage repair. The metabolic adaptations caused by inflammation illustrate the intimate relationship between our immune system and metabolism. This relation is designed for the short term. In a chronic state it eventually causes the metabolic syndrome and its sequelae. We are ourselves the cause of the chronicity. Our current Western lifestyle contains many false inflammatory triggers and is also characterized by a lack of inflammation suppressing factors.

The authors list many familiar components of the Western lifestyle that can cause chronic systemic low-grade inflammation, “which in turn leads to chronically compromised insulin sensitivity, compensatory hyperinsulinemia and, eventually, the diseases related to the metabolic syndrome”:

  • the consumption of saturated fatty acids and industrially produced trans fatty acids
  • a high ω6/ω3 fatty acid ratio
  • a low intake of long-chain polyunsaturated fatty acids (LCP) of the ω3 series (LCPω3) from fish (EPA and DHA are most important)
  • a low status of vitamin D and vitamin K and magnesium
  • the “endotoxemia” of a high-fat low-fiber diet
  • the consumption of carbohydrates with a high glycemic index and a diet with a high glycemic load
  • a disbalance between the many micronutrients that make up our antioxidant/pro-oxidant network
  • a low intake of fruit and vegetables
  • an abnormal composition of the bacterial flora in the mouth, gut, and gingivae
  • chronic stress
  • smoking, second-hand smoke, and environmental pollution
  • insufficient physical activity
  • insufficient sleep
  • excessive alcohol consumption
  • low fiber intake
  • meat from domesticated animals
  • obesity

“Homo sapiens emerged about 160,000 years ago in East-Africa.”

In contrast to some (e.g., John Hawks?) who believe we are rapidly evolving, these authors think that our genome, “with an average effective mutation rate of 0.5% per million years,” still overwhelmingly reflects the Paleolithic era.

They support their contentions with 334 references.

Steve Parker, M.D.

Heart Attacks Hinge on LDL Cholesterol Particle Number (LDL-P)

medical clearance, treadmill stress test

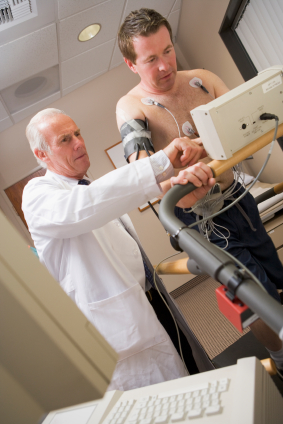
This treadmill stress test is looking for hidden heart disease

…according to Drs. Thomas Dayspring and James Underberg. I don’t know if these guys are right or not. I bet it’s more complicated than LDL particle number. I’m always skeptical of grand unification theories.

People with diabetes tend to have shorter life spans than average. One reason is a predisposition to heart disease, specifically coronary artery disease that leads to heart attacks.

Most heart attacks (aka myocardial infarctions) do indeed seem to be caused by acute rupture of an atherosclerotic plaque that’s been present for years. Two key questions are:

  1. What causes the plaque?
  2. Why causes it to rupture?

Underberg and Dayspring write:

The only absolute requirement for plaque development is the presence of cholesterol in the artery: although there are additional heart risk factors like smoking, hypertension, obesity, family history, diabetes, kidney disease, etc., none of those need to be present. Unfortunately, measuring cholesterol in the blood, where it cannot cause plaque, until recently has been the standard of risk-testing. That belief was erroneous and we now have much better biomarkers to use for CV risk-assessment. The graveyard and coronary care units are filled with individuals whose pre-death cholesterol levels were perfect. We now understand that the major way cholesterol gets into the arteries is as a passenger, in protein-enwrapped particles, called lipoproteins.

Particle entry into the artery wall is driven by the amount of particles (particle number) not by how much cholesterol they contain. Coronary heart disease is very often found in those with normal total or LDL-cholesterol (LDL-C) levels in the presence of a high LDL particle number (LDL-P). By far, the most common underlying condition that increases LDL particle concentration is insulin resistance, or prediabetes, a state where the body actually resists the action of the sugar controlling hormone insulin. This is the most common scenario where patients have significant heart attack risk with perfectly normal cholesterol levels. The good news is that we can easily fix this, sometimes without medication. The key to understanding how comes with the knowledge that the driving forces are dietary carbohydrates, especially fructose and high-fructose corn syrup. In the past, we’ve often been told that elimination of saturated fats from the diet would help solve the problem. That was bad advice. The fact is that until those predisposed to insulin resistance drastically reduce their carbohydrate intake, sudden deaths from coronary heart disease and the exploding diabetes epidemic will continue to prematurely kill those so afflicted.

***

 And for goodness’ sake, if you want to live longer, start reducing the amount of dietary carbohydrates, including bread, potatoes, rice, soda and sweetened beverages (including fruit juices), cereal, candy – the list is large).

Read the whole enchilada.

Offhand, I don’t recall any clinical study looking at LDL cholesterol particle number in folks who switched to a paleo diet. Given the prominence of coronary heart disease, I’m sure Dayspring and Underberg would favor a low-carb version of the paleo diet for anyone going the paleo route. Here’s my version of low-carb paleo.

Underberg and Dayspring don’t mention LDL particle size, such as small/dense and large/fluffy; the former are thought by many to be much more highly atherogenic, while the latter may not be at all. Is this idea outdated?

Whoever figures out the immediate cause of plaque rupture and how to reliably prevent it will win a Nobel Prize in Medicine.

Steve Parker, M.D.

About Dayspring and Underberg:

Thomas Dayspring MD, FACP, FNLA   Director of Cardiovascular Education, The Foundation for Health Improvement and Technology, Richmond, VA. Clinical Assistant Professor of Medicine, University of Medicine and Dentistry of New Jersey, New Jersey Medical School.

James Underberg MD, FACP, FNLA   Clinical Assistant Professor of Medicine in the Division of General Internal Medicine at NYU Medical School and the NYU Center for Cardiovascular Disease Prevention . Director of the Bellevue Hospital Primary Care Lipid Management Clinic.

h/t Dr. Axel Sigurdsson

“Rich the Diabetic” Is Sold On the Paleo Lifestyle

Click for his testimonial from 2012. Rich is a type 1 diabetic (he uses “diabetic” rather than “person with diabetes”). Rich was influenced by Tom Naughton, Robb Wolf, and Mark Sisson. He dropped his hemoglobin A1c by 2.5 over his first six months of paleo eating. This snippet explains some of his lifestyle changes:

The only thing I changed back in March, was starting to live paleo.  I’ve always worked out regularly, so I’m not really accounting my exercise in this improvement.  I’m probably about 70% paleo overall, but at home I’m 100% paleo.  My home no longer has any processed foods that come in a box, can, or sack.  I buy whole foods (fruits and lots of veggies), a little frozen veggies for convenience and storage time, lots of meat, no dairy, and lots of olive and coconut oil.  I cook a lot now, which means I do a lot more dishes than I want to, but it’s been worth it.

Read the rest.

Dr. Richard Bernstein Not a Fan of Insulin Pumps

Click for details at DiabetesHealth. Dr. Bernstein is a type 1 diabetic and one of the first users of a home blood glucose monitor. He’s most famous for recommending very-low-carb eating for folks with diabetes, in his book Diabetes Solution. An excerpt from DiabetesHealth:

I spent a month in a major insulin pump center and saw several things. Many of the female patients seemed to have wings on their sides where the pump tubing was inserted and they got lipohypertrophy [overgrown fat tissue] from localized injections, but that was the least of it. None of them actually had remotely normal blood sugars.

Another Study Links Diabetes and Prediabetes With Alzheimer’s Dementia

…according to an article at MedPageToday. A cohort of patients with mild to moderate Alzheimer’s were found to have unexpectedly high rates of impaired glucose tolerance or outright type 2 diabetes. We don’t know for sure if impaired glucose metabolism is a cause of dementia, or if some other factor links the two conditions. Until we have that answer, if I had impaired glucose metabolism, I’d work to improve it with loss of excess weight, exercise, and low-carb eating.

Here’s another article I wrote wondering if diabetes causes dementia.

Recommended Periodic Evaluations and Treatment Goals for Diabetics

If you don't like your physician, find a new one

If you don’t like your physician, find a new one

So, you’ve got diabetes. I’m sorry. You’ve got a heck of a lot of medical information to master.

Unless you have a good diabetes specialist physician on your team, you may not be getting optimal care. Below are some guidelines you may find helpful. The goal is to prevent diabetes complications. Many primary care physicians will not be up-to-date on the guidelines. Don’t hesitate to discuss them with your doctor. Nobody, not even your doctor, cares as much about your health as you do.

Annual Tests

The American Diabetes Association (ADA) recommends the following items be done yearly (except as noted) in non-pregnant adults with diabetes. (Incidentally, I don’t necessarily agree with all ADA guidelines.) The complete ADA guidelines are available on the Internet.

  • Lipid profile (every two years if results are fine and stable)
  • Comprehensive foot exam
  • Screening test for distal symmetric polyneuropathy: pinprick, vibration, monofilament pressure sense
  • Serum creatinine and estimate of glomerular filtration rate (MDRD equation)
  • Test for albumin in the urine, such as measurement of albumin-to-creatinine ratio in a random spot urine specimen
  • Comprehensive eye exam by an ophthalmologist or optometrist (if exam is normal, every two or three years is acceptable)
  • Hemoglobin A1c at least twice a year, but every three months if therapy has changed or glucose control is not at goal
  • Flu shots

Other Vaccinations, Weight Loss, Diabetic Diet, Prediabetes, Alcohol, Exercise, Etc.

Additionally, the 2013 ADA guidelines recommend:

  • Pneumococcal vaccination. “A one time re-vaccination is recommended for individuals >64 years of age previously immunized when they were <65 years of age if the vaccine was administered >5 years ago.” Also repeat the vaccination after five years for patients with nephrotic syndrome, chronic kidney disease, other immunocompromised states (poor ability to fight infection), or transplantation.
  • Hepatitis B vaccination to unvaccinated adults who are 19 through 59 years of age.
  • Weight loss for all overweight diabetics. “For weight loss, either low-carbohydrate, low-fat calorie-restricted, or Mediterranean diets may be effective in the short-term (up to two years).” For those on low-carb diets, monitor lipids, kidney function, and protein consumption, and adjust diabetic drugs as needed. The optimal macronutrient composition of weight loss diets has not been established. (Macronutrients are carbohydrates, proteins, and fats.)
  • “The mix of carbohydrate, protein, and fat may be adjusted to meet the metabolic goals and individual preferences of the person with diabetes.” “It must be clearly recognized that regardless of the macronutrient mix, total caloric intake must be appropriate to weight management goal.”
  • “A variety of dietary meal patterns are likely effective in managing diabetes including Mediterranean-style, plant-based (vegan or vegetarian), low-fat and lower-carbohydrate eating patterns.”
  • “Monitoring carbohydrate, whether by carbohydrate counting, choices, or experience-based estimation, remains a key strategy in achieving glycemic control.”
  • Limit alcohol to one (women) or two (men) drinks a day.
  • Limit saturated fat to less than seven percent of calories.
  • During the initial diabetic exam, screen for peripheral arterial disease (poor circulation). Strongly consider calculation of the ankle-brachial index for those over 50 years of age; consider it for younger patients if they have risk factors for poor circulation.
  • Those at risk for diabetes, including prediabetics, should aim for moderate weight loss (about seven percent of body weight) if overweight. Either low-carbohydrate, low-fat calorie-restricted, or Mediterranean diets may be effective in the short-term (up to 2 years). Also important is exercise: at least 150 minutes per week of moderate-intensity aerobic activity. “Individuals at risk for type 2 diabetes should be encouraged to achieve the U.S. Department of Agriculture (USDA) recommendation for dietary fiber (14 g fiber/1,000 kcal) and foods containing whole grains (one-half of grain intake).” Limit intake of sugar-sweetened beverages.
  • “Adults with diabetes should be advised to perform at least 150 min/week of moderate-intensity aerobic physical activity (50–70% of maximum heart rate), spread over at least 3 days/week with no more than two consecutive days without exercise. In the absence of contraindications, adults with type 2 diabetes should be encouraged to perform resistance training at least twice per week.”
  • Screening for coronary artery disease before an exercise program is depends on the physician judgment on a case-by-case basis. Routine screening is not recommended.
Steve Parker MD, low-carb diet, diabetic diet

Olives, olive oil, and vinegar: classic Mediterranean foods

Clearly, some of my dietary recommendations conflict with ADA guidelines. The paleo diet isn’t even on their radar screen. The experts assembled by the ADA to compose guidelines were well-intentioned, intelligent, and hard-working. The guidelines are supported by 528 scientific journal references. I greatly appreciate the expert panel’s work. We’ve simply reached some different conclusions. By the same token, I’m sure the expert panel didn’t have unanimous agreement on all the final recommendations. I invite you to review the dietary guidelines yourself, discuss with your personal physician, then decide where you stand.

General Blood Glucose Treatment Goals

The ADA in 2013 suggests these therapeutic goals for non-pregnant adults:

  • Fasting blood glucoses: 70 to 130 mg/dl (3.9 to 7.2 mmol/l)
  • Peak glucoses one to two hours after start of meals: under 180 mg/dl (10 mmol/l)
  • Hemoglobin A1C: under 7%
  • Blood pressure: under 140/80 mmHg
  • LDL cholesterol: under 100 mg/dl (2.6 mmol/l). (In established cardiovascular disease: <70 mg/dl or 1.8 mmol/l may be a better goal.)
  • HDL cholesterol: over 40 mg/dl (1.0 mmol/l) for men and over 50 mg/dl (1.3 mmol/l) for women
  • Triglycerides: under 150 mg/dl (1.7 mmol/l)

The American Association of Clinical Endocrinologists (AACE) in 2011 proposed somewhat “tighter” blood sugar goals for non-pregnant adults:

  • Fasting blood glucoses: under 110 mg/dl (6.11 mmol/l)
  • Peak glucoses 2 hours after start of meals: under 140 mg/dl (7.78 mmol/l)
  • Hemoglobin A1C: 6.5% or less

The ADA reminds clinicians, and I’m sure the AACE guys agree, that diabetes control goals should be individualized, based on age and life expectancy of the patient, duration of diabetes, other diseases that are present, individual patient preferences, and whether the patient is able to easily recognize and deal with hypoglycemia. I agree completely.

Steve Parker, M.D.

Dr. Richard Bernstein on the Paleo Diet for Diabetes

DiabetesHealth has a brief article on Dr. Bernstein’s view of the Paleolithic diet. They quote him thusly:

There’s no way the ADA [American Diabetes Association] diet or any high-carbohydrate and low-fat diet will enable you to control blood sugars. It turns out that the kind of diet I recommend is essentially a Paleolithic diet, which is what humanity evolved on. Our ancestors did not have bread, wheat, sweet fruits, and all of the delicious things that we have today. These have been specially manufactured for us nowadays. For food, our ancestors had a paucity of roots, some leaves, and principally meat to eat. If they lived near the shore, they had fish.

Read the rest.

Dr. Deans on the Care and Feeding of Zoo Humans

When I explain to my patients why paleo-style eating may be the healthiest diet, I use a thought experiment. It goes like this. You find an injured or weak bird in your yard and you hope to nurse it back to health. First you need to identify the bird’s species since that will tell you what to offer as food. Most birds specialize in what they’re able to eat in order to survive and thrive. Some eat only seeds, leaves, or other plant matter. Others eat only specific insects, grubs, or worms. You get the idea. Get the food choice wrong, and you’ve got a dead bird on your hands.

Emily Deans gives a similar rationale for the paleo diet at her Psychology Today blog. She writes:

At the Cleveland Metroparks Zoo in 2005, a gorilla died of heart disease at the age of 21. Heart disease is the leading killer of captive gorillas, who also seem to be vulnerable to developing ulcerative colitis, and autoimmune disease of the gut. That led researchers to consider changing the gorilla diets, which at typical zoos had been filled with processed animal chows, meat, yogurt, milk, eggs, bread, and cereal grains along with large amounts of various fruits and vegetables. Free ranging wild gorillas, on the other hand, eat mostly immature leaves, stems, some bark, saplings, wild fruits, insects, and some small animals. The diet of the gorillas in the wild has an incredibly high fiber content, which is used as food by the may trillions of bacteria in the gorilla’s extremely long gut. The fiber is transformed into a short chain fatty acid called butyrate that is important for colonic health and may be the reason (along with the cereal grains and other unusual foods) the captive gorillas developed ulcerative colitis.

Read the rest.